

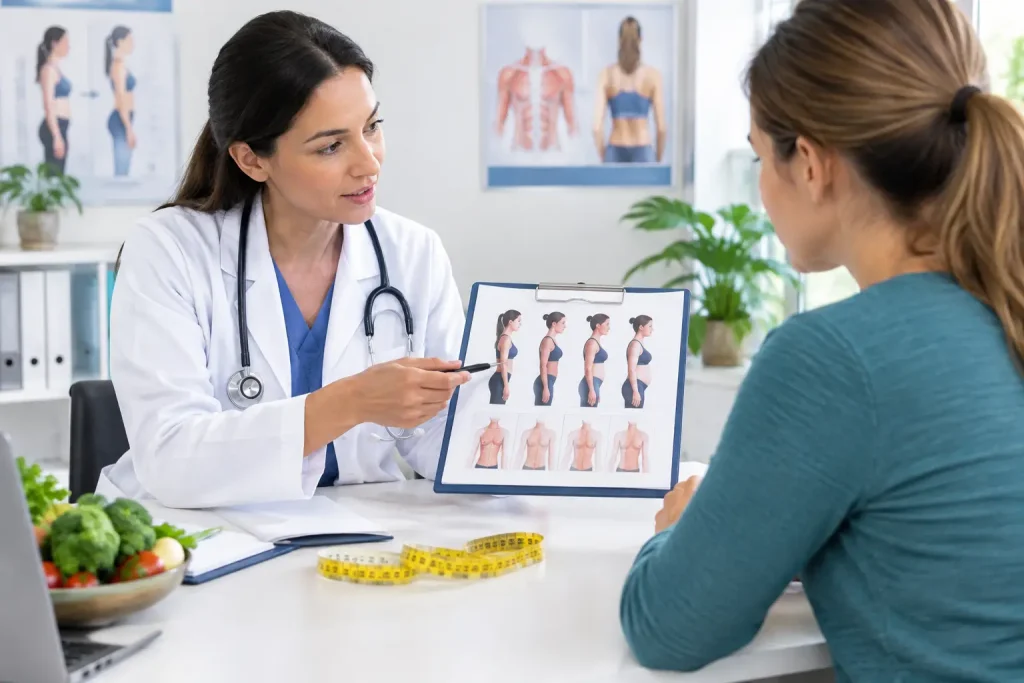
A smaller number on the scale can feel transformative, yet the mirror may reveal a change many patients did not expect: breasts that appear flatter, softer, lower, or less symmetrical. How does weight loss affect breast shape? The answer lies in the relationship between fat volume, glandular tissue, skin elasticity, and the supporting structures that give the breast its position on the chest.
For some women, weight loss creates only a subtle reduction in cup size. For others, particularly after substantial or rapid loss, it can alter the breast silhouette enough to affect clothing choices, body confidence, and the way the torso appears in proportion. These changes are not a failure of weight loss. They are a normal result of how breast tissue and skin respond to a changing body.
How Weight Loss Affects Breast Shape
Breasts are composed of fatty tissue, glandular tissue, connective tissue, skin, and the nipple-areola complex. The proportion of fat and glandular tissue differs from one person to another. Because fatty tissue often decreases with overall body weight, breasts may lose fullness as the body becomes leaner.
The visible result is not always simply a smaller breast. When volume decreases inside a skin envelope that has expanded over time, the skin may not contract completely. This can leave the breast looking deflated, with less upper-pole fullness and more looseness in the lower portion of the breast. The nipple may remain in a favorable position, or it may begin to point downward as the skin and internal support stretch.
Weight loss can also make pre-existing asymmetry more noticeable. Nearly all breasts have small natural differences in size, projection, and nipple position. Once volume is reduced, those differences may become more apparent, especially when one breast contains a higher proportion of fatty tissue than the other.
Volume Loss Is Only One Part of the Picture
A loss of breast volume can occur without significant sagging, particularly in younger patients with resilient skin and modest weight change. Conversely, a patient may have enough remaining breast tissue but still feel that her breasts look empty or low because the skin envelope has lost support.
This distinction matters when considering aesthetic options. Adding volume does not always correct drooping, and lifting the breast does not always restore upper fullness. The most refined surgical planning begins by identifying whether the primary concern is volume, skin laxity, nipple position, breast width, asymmetry, or a combination of these factors.
Why Some Breasts Change More Than Others
The same amount of weight loss can produce very different changes from one patient to the next. Genetics play a meaningful role in skin quality, breast composition, and the strength of the connective tissues that support the breast.
Age also influences the response. Over time, collagen and elastin production decline, making it less likely that stretched skin will retract fully after volume loss. Pregnancy and breastfeeding can add further changes, as breasts enlarge and then involute, sometimes repeatedly. Significant fluctuations in weight can have a similar effect by stretching the skin through multiple cycles of expansion and reduction.
The pace and total amount of weight loss matter as well. A gradual 10-pound loss may create a barely visible change, while major weight loss after bariatric surgery, medication-assisted treatment, or a sustained lifestyle transformation may leave more pronounced excess skin and volume loss. Smoking, sun exposure, and individual healing characteristics can also affect skin elasticity.
Common Changes After Significant Weight Loss
Patients often describe a recognizable set of concerns after their weight stabilizes. These may include a flatter upper breast, a longer distance from the collarbone to the nipple, loose skin along the lower breast, widened breasts that sit farther apart, or a nipple-areola complex that appears lower than before.
In aesthetic assessment, breast ptosis refers to a breast in which the nipple has descended relative to the fold beneath the breast. Pseudoptosis is slightly different: the nipple may still sit at an appropriate height, while most of the breast tissue has settled below the fold. This distinction is technical, but it is central to choosing the right procedure.
A breast that appears deflated after weight loss is not necessarily best treated with a larger implant. In some cases, an implant alone can add projection but leave loose skin or a low nipple unaddressed. In others, a lift without added volume may create a youthful and elegant shape using the patient’s existing tissue. Proportion, not a standardized cup size, should guide the decision.
Can Exercise Restore Breast Fullness?
Chest exercises can strengthen the pectoral muscles beneath the breasts and improve the contour of the upper torso. They cannot replace lost breast fat or glandular tissue, and they cannot tighten significantly stretched breast skin. A stronger chest may improve posture and create a more supported visual frame, but it does not reverse true volume loss or correct nipple descent.
Supportive bras, thoughtful garment fitting, and stable nutrition can also make a meaningful difference in comfort and daily confidence. These measures are valuable, especially while weight is still changing. However, they do not alter the underlying architecture of the breast.
Non-surgical skin treatments may modestly improve skin texture in selected cases, but they cannot reliably lift a breast or recreate substantial volume. Patients deserve a clear distinction between improvements in skin quality and a structural reshaping of the breast.
Surgical Options for Post-Weight-Loss Breast Changes
For patients whose weight has been stable and who wish to restore proportion, breast reshaping can be tailored with exceptional precision. The right approach depends on anatomy, skin quality, desired size, lifestyle, and the degree of change after weight loss.
Breast Lift
A breast lift, also called mastopexy, reshapes and elevates the breast by removing excess skin, repositioning the nipple-areola complex, and redistributing existing breast tissue. It is often an excellent option for women who are satisfied with their current breast volume but want a firmer, more elevated contour.
The trade-off is scarring. Lift scars are placed strategically and mature over time, but they are an unavoidable part of a true surgical lift. Their pattern depends on how much correction is needed, ranging from a scar around the areola to vertical and, when necessary, horizontal scars in the breast crease.
Breast Lift With Implants
When both lifting and volume restoration are needed, a breast lift can be combined with implants. This approach may improve upper-pole fullness, projection, and overall balance while addressing loose skin and low nipple position.
The artistic challenge is restraint. An implant that is too large for the skin envelope can create tension, compromise long-term shape, or contribute to recurrent drooping. A sophisticated plan considers breast base width, soft-tissue coverage, chest proportions, and the patient’s preferred silhouette rather than relying on volume alone.
Breast Lift With Fat Transfer
Fat transfer uses purified fat from another area of the body to provide subtle, natural-feeling volume. It can be appealing for patients who want gentle upper-pole enhancement without an implant. Not all transferred fat survives, and multiple sessions may be required when a more visible increase is desired.
Fat transfer is particularly useful when the goal is refinement rather than dramatic enlargement. It may be combined with a lift in carefully selected patients, allowing shape, softness, and proportion to be addressed together.
Auto-Augmentation Mastopexy
For some post-weight-loss patients, existing breast tissue can be reshaped and repositioned to create volume in the upper breast without an implant. Known as auto-augmentation mastopexy, this technique uses the patient’s own tissue strategically rather than simply removing loose skin.
Its suitability depends on having enough remaining tissue of appropriate quality. It cannot create volume where there is very little tissue, but for the right patient it can offer an elegant, implant-free result.
When Is the Right Time to Consider Breast Reshaping?
The ideal time is usually after weight has remained stable for several months and the patient feels confident that further significant loss is unlikely. Operating during active weight loss can make the final breast shape less predictable because continued volume reduction may alter the result.
A consultation should include a careful examination of skin elasticity, nipple position, breast volume, chest wall anatomy, asymmetry, and medical history. At a premium aesthetic practice such as Dr. Güncel Öztürk’s, this assessment is also a design process: the goal is not simply to make the breast larger or higher, but to create a proportionate form that complements the shoulders, waist, hips, and the patient’s individual aesthetic.
Patients should also discuss future pregnancy plans, as pregnancy can change breast volume and skin quality again. While breast surgery does not automatically prevent breastfeeding, certain techniques and individual anatomy may affect it. This is a personal consideration that belongs in preoperative planning.
Weight loss can change breast shape, but it does not define what your body should look like next. Once your weight is stable, a thoughtful evaluation can clarify whether your best path is simply time and support, a non-surgical confidence strategy, or a carefully designed surgical refinement that feels authentic to your new silhouette.







